
Evidence reviewed: 21 August 2026
Author: ExtolX Editorial Team
This is an educational overview of published research, not medical advice.
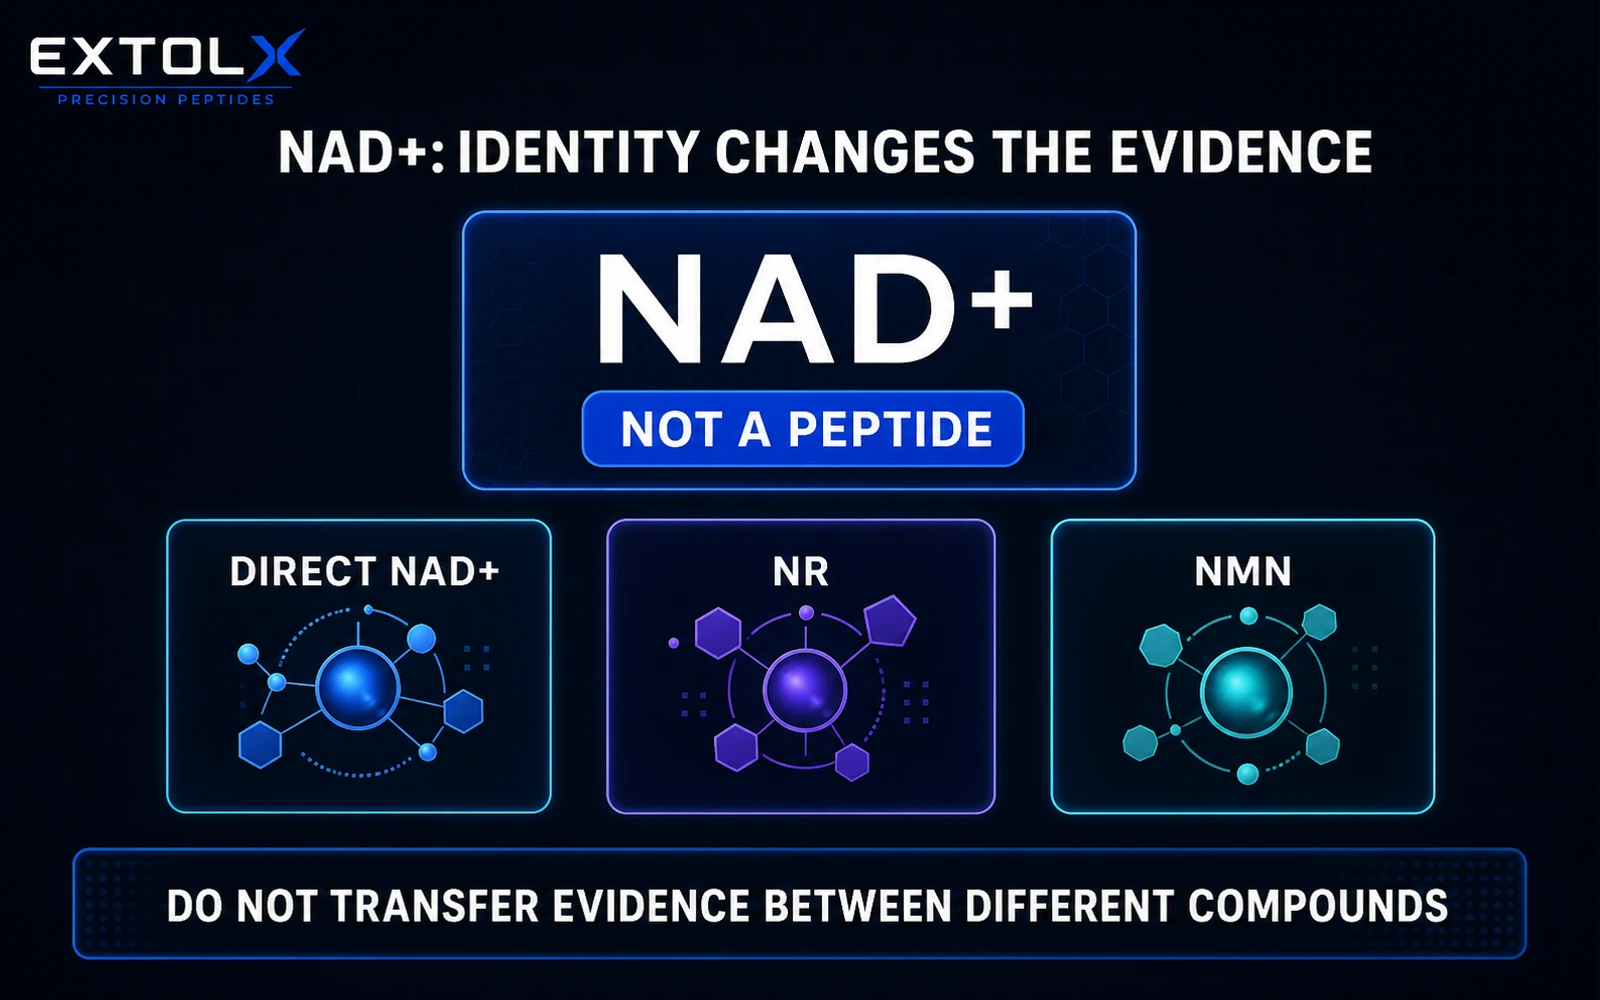
NAD+ is a molecule that cells use in energy transfer and enzyme reactions. It is not a peptide. Although human studies have tested NAD+-related precursors such as NR and NMN, direct NAD+ has a smaller and less consistent human research base.
The short version
- NAD+ is nicotinamide adenine dinucleotide, a cellular cofactor rather than a peptide.
- It helps transfer electrons in metabolism and is also consumed by enzymes involved in cell signalling and repair.
- Direct NAD+, nicotinamide riboside (NR), nicotinamide mononucleotide (NMN) and niacin are different interventions.
- Human studies of oral precursors are more developed than studies of direct NAD+, but physiological benefits remain inconsistent.
- Small direct-infusion studies can describe metabolites or tolerability; they do not establish broad anti-ageing, energy or health benefits.
- Raising a blood metabolite is not the same as improving a clinical outcome.
What is NAD+?
NAD+ stands for nicotinamide adenine dinucleotide. It is a cofactor: a small molecule that helps enzymes carry out chemical reactions.
Unlike the other subjects in much of the ExtolX Research Library, NAD+ is not a peptide and is not made from a short chain of amino acids. Its biology and evidence should therefore be assessed on their own terms.
What does NAD+ do in cells?
The practical point is that NAD+ has more than one cellular role. In its NAD+/NADH pair, it transfers electrons during reactions involved in energy metabolism.
NAD+ is also used up by enzymes including sirtuins, PARPs and CD38. These enzymes take part in signalling, DNA-damage responses and other cellular processes. A central role in normal biology does not by itself show that supplying more NAD+ will improve a health outcome.
Are NAD+, NR and NMN interchangeable?
No. NR, NMN and niacin can contribute to pathways that make NAD+, but they are different molecules with different absorption, conversion and study records. Direct NAD+ is another separate intervention.
A study showing that one precursor changes a blood marker cannot be cited as though it directly tested NAD+. Even within precursor research, a measurable increase in an NAD+-related metabolite does not automatically produce a meaningful physiological benefit.
What does the evidence show?
Laboratory research
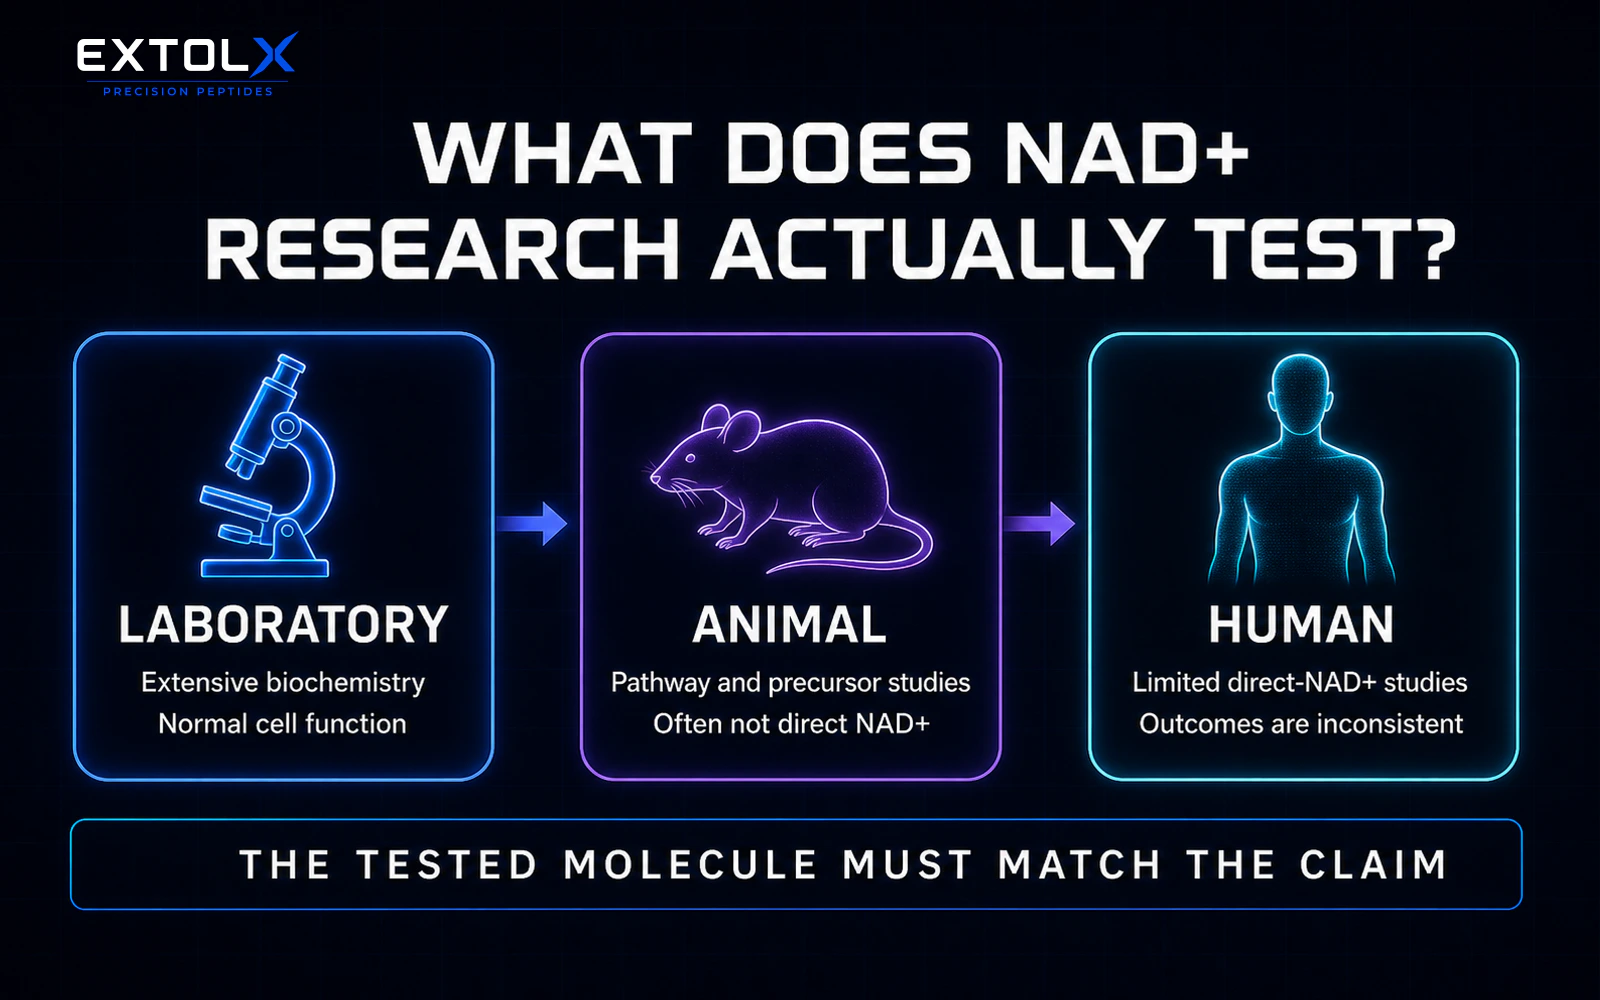
NAD+ biology is supported by extensive biochemical research. Laboratory studies explain its redox role, the enzymes that consume it and the pathways cells use to rebuild it.
This establishes that NAD+ is essential to normal cellular function. It does not establish that a particular external formulation improves energy, ageing or disease outcomes in humans.
Animal research
Animal studies have explored changes in NAD+ metabolism across ageing, metabolic stress and disease models. Much of this research uses precursors or manipulates enzymes in the NAD+ pathway rather than testing direct NAD+ itself.
Results can help identify mechanisms and promising measurements. They cannot be transferred automatically to people or from one NAD+-related compound to another.
Human research
A small pilot study of direct NAD+ infusion examined changes in circulating and urinary metabolites. It was useful for describing what could be measured during the study, but it was not designed to establish clinical effectiveness.
A 2026 retrospective report from a commercial clinic compared tolerability observations during NAD+ and NR infusions. Because it was retrospective, uncontrolled and based on routine clinic records, it cannot provide the certainty of a randomised trial.
Oral NR and NMN have a larger randomised human literature than direct NAD+. These studies often show that a precursor can alter NAD+-related blood measurements, while results for physical or clinical outcomes are mixed and depend on the population and outcome studied.
| Evidence level | What is available | Main limit |
|---|---|---|
| Laboratory | Extensive NAD+ biochemistry | Normal cellular importance does not prove an intervention benefit |
| Animal | Many pathway and precursor studies | Often not direct NAD+ and not directly transferable to people |
| Human | Small direct-NAD+ studies; more precursor trials | Direct evidence is limited and outcome benefits are inconsistent |
Where are evidence-transfer mistakes made?
- From normal biology to an intervention benefit: an essential cellular role does not show that supplying more improves a person’s health.
- From a precursor to direct NAD+: NR, NMN, niacin and NAD+ are not interchangeable study materials.
- From a blood marker to an outcome: a higher metabolite measurement does not prove better function or wellbeing.
- From a clinic record to a controlled trial: retrospective observations are vulnerable to missing information and bias.
What remains unknown?
- How direct NAD+ is distributed and processed across different human tissues.
- Which measured changes, if any, translate into meaningful physiological outcomes.
- How results vary by formulation, route, population and baseline NAD+ status.
- The longer-term safety profile of repeated direct exposure.
- Whether any proposed outcome is reproducible in well-controlled independent trials.
Regulatory context
NAD+ research material is not thereby authorised as a medicine; product classification depends on presentation, intended purpose and jurisdiction. A research-use label does not override the way a product is presented, promoted or used. Safety information from one formulation or jurisdiction cannot be transferred automatically to another.
What would better research look like?
Studies should identify the exact material being tested and keep direct NAD+, NR, NMN and other precursors separate. A registered randomised trial would need a suitable control, enough participants and outcomes selected before results are known.
Researchers should measure both exposure and outcomes that matter, report adverse events consistently and follow participants for an appropriate period. Independent replication is needed before a biomarker change can be connected confidently with a practical result.
Plain-English glossary
- Cofactor: A small molecule that helps an enzyme carry out a reaction.
- Redox reaction: A chemical reaction involving the transfer of electrons.
- NADH: The electron-carrying form paired with NAD+ in many metabolic reactions.
- Precursor: A substance the body can use in a pathway to make another substance.
- NR: Nicotinamide riboside, an NAD+ precursor.
- NMN: Nicotinamide mononucleotide, an NAD+ precursor.
- Retrospective study: Research that looks back at information already recorded rather than assigning conditions in advance.
Explore NAD+ research material
ExtolX NAD+ 500MG is supplied as research material. Its identity and analytical documentation should be assessed separately from evidence about NR, NMN, niacin or other NAD+-related compounds.
References and further reading
- Pilot study examining the metabolome during direct NAD+ infusion — PubMed
- Retrospective comparison of NAD+ and NR infusion tolerability — PubMed
- Systematic review of human NAD+-precursor research — PubMed
Research-use notice: ExtolX products are supplied strictly for legitimate laboratory research. They are not intended for human or veterinary use, consumption, diagnosis, treatment or prevention of disease.